
Skip to content
Artwork for Dr. John Campbell
EducationHealth & FitnessMedicine

Dr. John Campbell

Campbellteaching

Hello Everyone, My name is John Campbell and I am a retired Nurse Teacher and former clinical nurse based in England. I also do some teaching in Asia and Africa when time permits. These videos are to help students to learn the background to all forms of health care. My PhD focused on the development of open learning resources for nurses nationally and internationally. LinkedIn profile, https://www.linkedin.com/in/dr-john-campbell-5256223b/ Twitter, https://twitter.com/Johnincarlisle Disclaimer; These media including videos, book, e book, articles, podcasts are not peer-reviewed. They should never replace individual clinical judgement from your own health care provider. No media-based material on this channel is suitable for using as professional medical advice. All comments are also for educational purposed only and must never replace advice from your own health care provider

Play
  • 767 episodes
  • daily
  • Avg 24 min
  • English
Counted on this page — what you have heard stays on this device, so it is not something the list can be paged by.
  • October 5 · 28 min

    Heart deaths

    Write to YOUR MP, https://www.writetothem.com/?a=westminstermp https://twitter.com/ABridgen/status/1737475231386653113 Free download John’s textbooks in high res pdf. https://drjohncampbell.co.uk Check out Campbell's Physiology Notes Dr John Campbell Sold by author on eBay! https://www.ebay.co.uk/itm/155780745424?mkcid=16&mkevt=1&mkrid=711-127632-2357-0&ssspo=K6raxMZrQnm&sssrc=4429486&ssuid=K6raxMZrQnm&var=&widget_ver=artemis&media=EMAIL ‘a threatening phone call’ https://www.telegraph.co.uk/news/2023/11/08/how-astrazeneca-vaccine-was-shelved/ 8th November 2023 In March 2021, The Telegraph was one of the first newspapers to imply a causal link between the jab and blood clots after Norwegian scientists suggested a possible mechanism. On the day we published the story we received a threatening phone call from a senior official at the MHRA warning that The Telegraph would be banned from future briefings and press notices if we did not soften the news. https://www.gov.uk/government/organisations/medicines-and-healthcare-products-regulatory-agency From FDA to MHRA: are drug regulators for hire? https://www.bmj.com/content/377/bmj.o1538 June 2022 Industry money saturates the globe’s leading regulators. The BMJ found that the majority of regulators’ budget—particularly the portion focused on drugs—is derived from industry fees Another well-known Cambridge academic got in touch to complain about our “disgraceful fear-mongering headline” on the story, claiming that it would discourage vaccine uptake and cost lives. We politely pointed out that hiding the facts from people was not helpful and could also cost lives. The academic did not respond. In February this year, TikTok removed an audio clip in which I discussed whether the benefit of vaccination was worth the risks for young people, claiming it had breached community guidelines. After we showed that the Government’s own website acknowledges the link, the clip was reinstated. All of this shows a troubling paternalism in government, academia and some media outlets who believe that the public is not capable of weighing up the pros and cons of medical interventions and so must be shielded from the truth. Excess mortality in England post Covid-19 pandemic: implications for secondary prevention https://www.sciencedirect.com/science/article/pii/S2666776223002211?via%3Dihub Many countries, including the UK, have continued to experience an apparent excess of deaths long after the peaks associated with the COVID-19 pandemic in 2020 and 2021. Numbers of excess deaths estimated in this period are considerable. The UK Office for National Statistics (ONS) has calculated that there were 7.2% or 44,255 more deaths registered in the UK in 2022 OECD, UK https://stats.oecd.org/index.aspx?queryid=104676 Excess deaths in 2022, 52,514 (9.26%) This persisted into 2023 with 8.6% or 28,024 more deaths registered in the first six months of the year than expected. OECD, UK, weeks 1 – 44, 2023 Excess deaths, 49,389 (9.44%) The causes of these excess deaths are likely to be multiple and could include the direct effects of Covid-19 infection, acute pressures on NHS acute services resulting in poorer outcomes from episodes of acute illness, and disruption to chronic disease detection and management. Further analysis by cause and by age- and sex-group may help quantify the relative contributions of these causes. Office for Health Improvement and Disparities 3rd June 2022 to 30th June 2023 Excess deaths for all causes were relatively greatest for 50–64 year olds (15% higher than expected) 11% higher for 25–49 and under 25 year olds, and about 9% higher for over 65s Several causes 3rd June 2022–30th June 2023 All cardiovascular diseases, 12% Heart failure, 20% Ischaemic heart disease, 15 Liver diseases, 19% Acute respiratory infections, 14% Diabetes, 13% For Learn more about your ad choices. Visit megaphone.fm/adchoices

  • October 5 · 13 min

    Hunger for quality science and medicine

    Professor Angus Dalgleish, (Fellow of the Royal College of Physicians, Fellow of the Royal College of Pathologists, Fellow of Medical Science.) Professor Dalgleish is a highly experienced doctor, physician, medical teacher, medical author and researcher with over 500 primary research publications. He was also a pioneering researcher into HIV/AIDS. Here we discuss the recently observed changes in cancer presentations and deaths. Some of the discussion considers this research paper noting excess cancer deaths in Japan. Increased Age-Adjusted Cancer Mortality After the Third mRNA-Lipid Nanoparticle Vaccine Dose During the COVID-19 Pandemic in Japan https://www.cureus.com/articles/196275-increased-age-adjusted-cancer-mortality-after-the-third-mrna-lipid-nanoparticle-vaccine-dose-during-the-covid-19-pandemic-in-japan#!/ Gibo M, Kojima S, Fujisawa A, et al. (April 08, 2024) Increased Age-Adjusted Cancer Mortality After the Third mRNA-Lipid Nanoparticle Vaccine Dose During the COVID-19 Pandemic in Japan. Cureus 16(4): e57860. DOI 10.7759/cureus.57860 Conclusions Statistically significant increases in age-adjusted mortality rates of all cancer and some specific types of cancer, namely, ovarian cancer, leukemia, prostate, lip/oral/pharyngeal, pancreatic, and breast cancers, were observed in 2022 after two-thirds of the Japanese population had received the third or later dose of SARS-CoV-2 mRNA-LNP vaccine. These particularly marked increases in mortality rates of these ERα-sensitive cancers may be attributable to several mechanisms of the mRNA-LNP vaccination, rather than COVID-19 infection itself or reduced cancer care due to the lockdown. Researchers have reported that the SARS-CoV-2 mRNA-LNP vaccine may pose the risk of development and progression of cancer. Several case reports have described cancer developing or worsening after vaccination and discussed possible causal links between cancer and mRNA-LNP vaccination. Learn more about your ad choices. Visit megaphone.fm/adchoices

  • October 5 · 28 min

    Simple, cheap, non toxic and ignored

    Professor of Oncology, Angus Dalgleish gives vital information on a repurposed drug he uses for his cancer patients, given at a very low dose. This is Low Dose Naltrexone. Check out the LDN trust website for much more, https://ldnresearchtrust.org Naltrexone at low doses (LDN) and its relevance to cancer therapy https://openaccess.sgul.ac.uk/id/eprint/114135/ Naltrexone was designed to inhibit opioid receptors without activating them and hence used to block the stimulatory effects of morphine and heroin. It was noted that in certain patients being treated with naltrexone for an opioid addiction many reported significant secondary benefit when being weaned off naltrexone. This group of patients had chronic inflammatory and autoimmune conditions and reported improvements whilst using the lower dosages of naltrexone. There have also been recent anecdotal reports of cancer resolution following the use of low doses of naltrexone (LDN). However, the mechanism of action is unclear. Areas covered We review three mechanisms through which LDN can influence cancer progression; namely, (a) antagonism of receptors to which LDN binds, which include toll-like receptors 7–9 that lead to IL-6 suppression b) modulation of immune function in patients; and c) direct inhibition of signaling pathways involved in cancer cell control, including the priming of pro-apoptotic pathways. Expert opinion Considering the increase in the number of anecdotal reports of activity, there will likely be a bigger drive toward using LDN in the oncological setting. These reports support clinical trials of LDN in cancer, especially when given in combination with certain chemotherapy. https://ldnresearchtrust.org/angus-dalgleish-md-role-ldn-management-cancer-2018-conference-ldn-low-dose-naltrexone Major clinical evidence on the use of low-dose naltrexone in the treatment of cancer: a systematic review https://www.researchgate.net/publication/384236060_Major_clinical_evidence_on_the_use_of_low-dose_naltrexone_in_the_treatment_of_cancer_a_systematic_review https://www.tandfonline.com/doi/full/10.1080/14737140.2022.2037426#abstractors :00 🍏 Discussion on Simple, Non-Toxic Health Solutions - The conversation begins with highlighting the neglect of simple, cheap, and non-toxic health solutions like iodine and vitamin D. - Emphasis is placed on differences in health outcomes between countries that consume iodine-rich foods, like seaweed, and those that do not, such as the US and UK, where breast cancer rates are higher. 05:00 💊 Frustration with Pharmacy Practices and Medication Access - The speakers express frustration over pharmacists' lack of knowledge regarding iodine and other non-toxic medications. - Experiences in pharmacies reveal a broader issue of doctors and patients being denied access to potentially beneficial treatments. 10:00 📉 Barriers in Medical Practice and Prescribing Authority - Discussion on the limitations imposed on medical professionals, preventing them from applying their knowledge to help patients fully. - Anecdotes highlight instances where doctors are unable to prescribe effective treatments, leading to a bureaucratic environment stifling innovation. 14:00 🌍 The Impact of Current Medical Education on Practice - A critique of contemporary medical education emphasizes its focus on guidelines over creative medical thinking. - Medical students are discouraged from expanding their understanding, which harms their ability to think critically and adapt medicine to patient needs. 18:00 🔄 Historical Insight into Treatment Innovations - The speaker reflects on the freedom and creativity that past medical practices allowed compared to current restrictions on innovative treatments. - An inspiring case of repurposing chemotherapy to address a severe arthritis condition showcases the potential benefits of adaptive medical practices. 20:00 💡 Low Dose Learn more about your ad choices. Visit megaphone.fm/adchoices

  • October 5 · 2 min

    Vitamin D

    Link to whole video, https://www.youtube.com/watch?v=0Ken0luasu0 Free download John’s textbooks in high res pdf. https://drjohncampbell.co.uk Order my Physiology Notes in hard copy if you live in the UK, https://www.ebay.co.uk/itm/154973392319?mkcid=16&mkevt=1&mkrid=711-127632-2357-0&ssspo=K6raxMZrQnm&sssrc=2047675&ssuid=&widget_ver=artemis&media=EMAIL Learn more about your ad choices. Visit megaphone.fm/adchoices

  • October 5 · 4 min

    Covert psychological manipulation

    This excellent scientific analysis of recent events continues in interview three of this series. Follow Dr. Craig on SubStack, https://drclarecraig.substack.com COVID, the untold story. So much more makes sense after this book and my first illuminating discussion with Dr. Craig. Get your copy in the UK here: https://www.amazon.co.uk/Expired-untold-Dr-Clare-Craig/dp/1739344707 For friends in the US get your copy here, https://www.amazon.com/Expired-untold-Dr-Clare-Craig/dp/1739344707 Have you ever felt the covid story did not entirely add up? Expired contains multiple eye-opening revelations about covid with compelling evidence that provides a coherent, sober and clear explanation that better fits the data we have so far. Meticulous research by pathologist Dr Clare Craig sheds light on the largely overlooked evidence of airborne virus transmission, examining twelve related beliefs on spread, lockdowns, asymptomatic infections, and masks. In addition, Expired champions the importance of Western ethical principles, damaged by pandemic actions and calls for their restoration. The covid debate has proved incredibly polarising. One side believed every intervention was saving lives, while the other emphasised the harms caused. Biased modelling based on a worst-case scenario led to fearful assumptions presented as fact. By dint of sheer repetition these ‘facts’ became unquestionable. Those scientists who dared to question were proclaimed dangerous. Welcome to Cloud-Covid-Land. Let’s bring back nuance. It’s time to return to reality." Learn more about your ad choices. Visit megaphone.fm/adchoices
  • October 5 · 16 min

    Tranquil and measured

    Thanks to all at Sky News Australia. Learn more about your ad choices. Visit megaphone.fm/adchoices

  • October 5 · 54 min

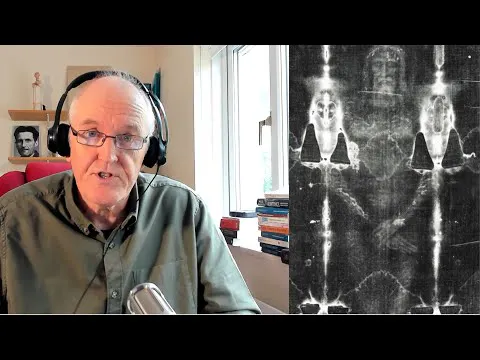
    Shroud: Scientific aspects

    With Dr. Richard Sorensen. Shroud of Turin Website, https://shroud.com/ Links for Rich, YouTube videos: "Biblical Mysteries Explained" https://www.youtube.com/@BiblicalMysteriesExplained Article sites: academia.edu, researchgate.net, richardsorensen.com, unholygrail.net/blog Watch this excellent film from David Rolfe, https://whocanhebe.com/Stream.html Watch this excellent film from David Rolfe, https://whocanhebe.com/Stream.html Link to download my PowerPoint, https://drjohncampbell.co.uk/ Shroud.com https://www.shroud.com/menu.htm Shroudphotos.com https://shroudphotos.com 3D Image https://shroud3d.com/introduction/3d-studies-of-the-shroud-of-turin-history/ Shroud fabric https://www.shroud.com/pdfs/ssi3233part3.pdf 3D reconstruction https://www.shroud.com/pdfs/ssi3233part3.pdf STURP conclusions https://www.shroud.com/78conclu.htm Study on radiocarbon result https://www.sciencedirect.com/science/article/abs/pii/S0040603104004745 New dating study on X ray scattering https://www.mdpi.com/2571-9408/5/2/47 Polon studies https://powo.science.kew.org/taxon/urn:lsid:ipni.org:names:210758-1 The Shroud of Turin is purported to be the burial shroud of Jesus Christ, and its authenticity has thus aroused intense and sometimes hostile debate between those who believe that the Shroud is authentic, and those who do not. Accepting or rejecting the authenticity of the Shroud is to many an issue of Christian or anti-Christian conviction. This is especially true for anti-Christians - if the Shroud is a fake it doesn't really affect the pro-Christian side, but if it is authentic then it is dramatic evidence in favor of it. So the Shroud of Turin is the most highly and intensively studied artifact in the history of the world. "Somewhere between 100,000 and 150,000 scientific man-hours have been spent on it, with the best analytical tools available” according to one source. 2. Please note that this is not about "proof" in the scientific sense because it is not possible to prove anything historical. For example, we can't prove that Julius Caesar lived, so likewise we can't prove that the Shroud was the burial cloth of Christ. What we can do is examine the evidence that supports or challenges that assertion. Regardless of conviction, those who seriously seek to study the Shroud should approach it with an open mind and suspend their religious persuasions as they examine the evidence, both pro and con. 3. Regardless of our convictions, it is right that we should question the Shroud and approach it with skepticism because the history of religious artifacts is filled with fraudulent attempts to make money at the expense of naïve worshippers. Many fake shrouds have been produced, and in 1902 a researcher claimed that there were forty-two medieval shrouds of Christ around Europe. However, they were not intended to deceive anyone - most were either simply pieces of cloth or artistic copies, and some of these “shrouds” still exist. Scientific challenges 1. There have been many attempts to debunk the Shroud, and perhaps the main one is in regard to dating. The Carbon 14 dating in 1988 indicated that the cloth was medieval (1260 to 1390 AD). However, it was later discovered that the pieces used for testing contained rewoven fibers that had been used to repair the cloth, so the C14 dating was discredited. A new non-destructive method of dating ancient textiles known as WAXS (wide-angle x- ray scattering) has been developed which operates by detecting the degree of structural degradation of threads from a cloth. Using that method a thread from the Shroud was dated to the same period as a line fragment from the siege of Masada (55-74 AD), so it places the Shroud in the era of Christ's death and resurrection, ca. 33 AD. No other grave cloth in history has ever had an image on it like the Shroud. Other scientific challenges have claimed that the Shroud was: 2 Learn more about your ad choices. Visit megaphone.fm/adchoices

  • October 5 · 2 min

    Keep learning

    Link to original video, https://www.youtube.com/watch?v=_6xBiyidQ9g Learn more about your ad choices. Visit megaphone.fm/adchoices

  • October 5 · 5 min

    Time to ready for omicron exposure

    Thanks to Eddie and DW news. Omicron is coming so we need to get our immune system into the best possible condition. Learn more about your ad choices. Visit megaphone.fm/adchoices

  • October 5 · 15 min

    More boosters, more contagion

    What the heck? But this is what the data shows, and this is not to mention the adverse reactions. Link to buy the book, https://covidthroughoureyes.com.au/products/covid-through-our-eyes-an-australian-story-of-mistakes-mistreatment-and-misinformation. Second part of this excellent talk with Professor Robert Clancy, doctor, immunologist, consultant physician, professor of pathology and professor of medicine, highly published medical researcher, author, teacher, doctor of science, doctor of philosophy, holder of the Australia Medal. Letters from Australia is Alison Bevege's Substack, https://lettersfromaustralia.substack.com/ Learn more about your ad choices. Visit megaphone.fm/adchoices

  • October 5 · 14 min

    Constructive UK data

    Less people going to hospital with Omicron infection compared to Delta infection. Apologies, I had a few technical problems with todays video Zoe update: Wednesday 22 December 2021 https://www.youtube.com/watch?v=CIGC310hPoI https://covid.joinzoe.com/post/everything-we-know-so-far-about-omicron https://joinzoe.com/learn/category/covid https://joinzoe.com/learn/new-omicron-variant 144,284 new daily symptomatic cases of COVID in the UK In people who have had at least 2 vaccine doses 56,346 new daily symptomatic cases in the UK 70% + cases in England are now Omicron The UK R value, 1.2 R value in London is 1.5. From 17,000 omicron cases Runny nose Headache Fatigue (either mild or severe) Sneezing Sore throat (NHS test and trace is not telling users of their Omicron status anymore) Report 50 - Hospitalisation risk for Omicron cases in England https://www.imperial.ac.uk/mrc-global-infectious-disease-analysis/covid-19/report-50-severity-omicron/ https://www.theguardian.com/world/2021/dec/22/risk-of-hospital-stay-40-lower-with-omicron-than-delta-uk-data-suggests Differences in the risk of hospitalisation between Omicron and Delta 1st to 14th December inclusive Analysed data from all PCR-confirmed SARS-CoV-2 cases in England Cases S-gene Target Failure (SGTF) and genetic data Omicron, n = 56,000 Delta, n = 269,000 Reduction in the risk of hospitalisation for Omicron relative to Delta infections Endpoint, any attendance at hospital 20-25% reduced risk Endpoint, hospitalisation lasting 1 day or longer 40-45% reduced risk These reductions must be balanced against the larger risk of infection with Omicron, due to the reduction in protection provided by both vaccination and natural infection. Intrinsic differences in severity between Omicron and Delta Omicron may result in slightly less severe disease From the few neither previously infected nor vaccinated, risk of hospitalisation, 11% lower for Omicron versus Delta Level of protection from previous infection Reduces the risk of any hospitalisation by 50% Reduces the risk of a hospital stay of 1+ days by 61% Risk of symptomatic infection with omicron More protection after PF/MD than AZ Hospitalisation risk by vaccination state AstraZenca (AZ) (doses 1 and 2) Omicron hazard ratios are lower than for Delta Pfizer or Moderna (PF/MD) (doses 1 and 2) Omicron hazard ratios are similar to those seen for Delta Conclusions, after at least 2 vaccine doses Protection against omicron infection has been largely lost Remain substantially protected against hospitalisation Does not substantially change Sage modelling Pointing to 3,000 daily hospitalisations in England at the peak next month Omicron cases in Scotland, Eave II study (Early Pandemic Evaluation and Enhanced Surveillance of COVID-19) https://www.sciencemediacentre.org/data-from-scotland-on-omicron-severity-from-the-eave-ii-study/ https://www.ed.ac.uk/usher/eave-ii/key-outputs/our-publications/severity-of-omicron-variant-of-concern-and-vaccine https://www.research.ed.ac.uk/en/publications/severity-of-omicron-variant-of-concern-and-vaccine-effectiveness- Hospital data from 23 November to 19 December Risk of hospitalisation, 70% lower with Omicron than Delta. 15 hospitalisations with Omicron Opposed to the 47 admissions from delta (Expected given the characteristics of those infected) First case of Omicron confirmed by viral sequencing was recorded in Scotland on November 23, 2021 By December 19, 2021, there were 23,840 S gene negative cases. These S gene negative cases were predominantly in the age group 20-39 (11,732; 49.2%). Reinfections, more than 10 times more likely with omicron Omicron positive cases that were reinfections, 7.6% Delta cases that were reinfections, 0.7% The third/booster vaccine dose was associated with a 57% reduction in the risk of symptomatic Learn more about your ad choices. Visit megaphone.fm/adchoices

  • October 5 · 16 min

    Extracting wisdom from the pandemic

    The retrospective report Technical report on the COVID-19 pandemic in the UK https://www.gov.uk/government/publications/technical-report-on-the-covid-19-pandemic-in-the-uk https://www.gov.uk/government/publications/technical-report-on-the-covid-19-pandemic-in-the-uk/list-of-chapters-authors-reviewers-and-contributors Baroness Hallett, independent public enquiry https://covid19.public-inquiry.uk Set up to look at the pandemic https://www.youtube.com/channel/UC9eFdKVwD1ARs3j9BSoGndw Online form launched 16th November https://share.covid19.public-inquiry.uk/s/your-experience Chapter 1, Section 6 https://www.gov.uk/government/publications/technical-report-on-the-covid-19-pandemic-in-the-uk/chapter-1-understanding-the-pathogen What was the duration of, naturally acquired immunity, and vaccine acquired immunity, and the risk of reinfection over time? By early 2020 Data emerged indicating that the majority of individuals infected with SARS-CoV-2 displayed an antibody response between 10 to 14 days after symptom onset Throughout the first half of 2021 Following natural infection Antibody detectable in saliva for at least 8 months, and in blood for at least 9 months. The presence of antibody, associated with a protective effect against infection, at least 7 to 10 months Cell-mediated immune response to SARS-CoV-2 was shown to be detectable up to 8 months after infection Reflections and advice for a future CMO or GCSA (for Chapter 1) https://www.gov.uk/government/publications/technical-report-on-the-covid-19-pandemic-in-the-uk/chapter-1-understanding-the-pathogen#questions-on-the-disease Point 1 Scientific and medical advice will often need to be formulated on the basis of limited data. Point 2 Understanding the pathogen and the disease was a global effort, particularly at the outset, and sharing data and expertise from the beginning was key. Point 3 Gaining a clear understanding of the pathogen and the disease required an array of cross-disciplinary studies to be initiated quickly. Point 4 Building on and adapting existing research systems and networks was usually much faster than setting up new systems, but strong leadership, direction and coordination are required. Point 5 Viral variants, population behaviours and population immunity changed significantly over time requiring continuation of studies. Not mentioned State secrecy needs to be eliminated, early, open sharing of all science. No more cover ups Dangerous gain of function research should stop Procurements should be on the basis of clinical and scientific need, not commercial interests Powerful international corporations should not be allowed to influence the agenda All pharmaceuticals should be considered, rather than just expensive ones Powerful international corporations and individuals should not be allowed to control public communications Early scientific peer review must be allowed and encouraged, based on fully disclosed primary data Primary anonymised data from clinical trials must be made public for the worlds clever people to process Scientists and doctors with ‘outlying views’ should be judged on the quality of the evidence they present Play the ball Further comments Britain a 'prolonged period' of excess deaths but not from coronavirus itself Heart disease and cancer, stayed away or could not access treatment Learn more about your ad choices. Visit megaphone.fm/adchoices

  • October 5 · 50 min

    Vaccine manufacture full interview

    Two different manufacturing processes. Pfizer covid vaccines for the clinical trials were mostly produced using manufacturing ‘process 1’ whereas the vaccines used for population vaccination were produced using a different ‘process 2’ Interview with Josh Guetzkow PhD Here is the BMJ link: https://www.bmj.com/content/378/bmj.o1731/rr-2 Josh's handle on X.com is @joshg99 and here is a link to a thread I did on P1 vs. P2: https://x.com/joshg99/status/1658421192326365185 Here is a link to my blog: https://researchrebel.substack.com/ Here are links to my posts on the Pfizer clinical trial https://researchrebel.substack.com/p/comirnaty-or-comirnaughty https://researchrebel.substack.com/p/how-long-did-the-pfizer-covid-vaccine https://researchrebel.substack.com/p/the-pfizer-vaccine-trial-was-not https://www.bmj.com/content/378/bmj.o1731/rr-2 https://www.nejm.org/doi/suppl/10.1056/NEJMoa2034577/suppl_file/nejmoa2034577_protocol.pdf https://twitter.com/joshg99/status/1658421192326365185 https://phmpt.org/wp-content/uploads/2023/04/125742_S1_M5_5351_c4591001-interim-mth6-report-body.pdf Learn more about your ad choices. Visit megaphone.fm/adchoices

  • October 5 · 26 min

    Natural cross immunity demonstrated

    Download free high-res copies of my two text books and the new posters. Any donations using this link help the work of campbell teaching. https://drjohncampbell.co.uk/ Massachusetts will give you a $75 gift card if you get vaccinated or boosted https://www.msn.com/en-us/news/us/massachusetts-will-give-you-a-2475-gift-card-if-you-get-vaccinated-or-boosted/ar-AA14H0pA $75 gift card for getting vaccinated against COVID-19, through Dec. 31st Adults and children alike, first dose, second dose, or booster shots. Boston Public Health Commission. https://support.google.com/youtube/answer/11161123 Vaccine safety: content alleging that vaccines cause chronic side effects, outside of rare side effects that are recognized by health authorities Efficacy of vaccines: content claiming that vaccines do not reduce transmission or contraction of disease Ingredients in vaccines: content misrepresenting the substances contained in vaccines Endemic common human coronaviruses About 20% of colds https://covid19.nj.gov/faqs/coronavirus-information/about-the-virus/how-are-the-coronaviruses-that-cause-the-common-cold-different-from-the-covid-19-virus https://www.cdc.gov/coronavirus/general-information.html Types 229E, NL63, OC43, and HKU1 usually cause mild to moderate upper-respiratory tract illnesses, like the common cold. runny nose sore throat headache fever cough general feeling of being unwell Human coronaviruses can sometimes cause lower-respiratory tract illnesses, such as pneumonia or bronchitis. This is more common in people with cardiopulmonary disease, weakened immune systems, infants, and older adults. Cross-reactive memory T cells associate with protection against SARS-CoV-2 infection in COVID-19 contacts https://www.nature.com/articles/s41467-021-27674-x https://www.webmd.com/lung/news/20220111/common-cold-covid-protection Cross-reactive immune responses Common cold coronaviruses and SARS-CoV-2 The frequency of baseline cross-reactive T cells, is correlated with the infection outcome following SARS-CoV-2 exposure, and we observe significantly higher frequencies of cross-reactive memory T cell responses in PCR-negative contacts. Here we assess 52 COVID-19 household contacts Studied peripheral blood mononuclear cells (Lymphocytes as opposed to neutrophils) T cells specific for spike, nucleocapsid, membrane, envelope and ORF1 SARS-CoV-2 epitopes, (Open Reading Frame, about a tenth of the viral genome) These T cells cross-react with human endemic coronaviruses. We observe higher frequencies of cross-reactivity Memory T cells cross reacted with nucleocapsid-specific antigens significantly Memory T cells did not seem to cross react with pre-existing spike-cross-reactive T cells Our results are thus consistent with pre-existing non-spike cross-reactive memory T cells protecting SARS-CoV-2-naïve contacts from infection, thereby supporting the inclusion of non-spike antigens in second-generation vaccines. China 66% per cent of over-80s are double vaccinated 68% per cent of over-60s have been boosted 1.3 to 2.1 million lives at risk https://www.telegraph.co.uk/global-health/science-and-disease/germany-urges-china-end-lockdowns-western-vaccines/?WT.mc_id=e_DM71323&WT.tsrc=email&etype=Edi_GHS_New_Tue_B&utmsource=email&utm_medium=Edi_GHS_New_Tue_B20221129&utm_campaign=DM71323 https://www.medscape.com/viewarticle/984612?src=wnl_edit_tpal&uac=127834AR&impID=4926650&faf=1 November up to 26th Cases 31,709 + 35,183 + 39,791 (only a few imported cases) Of the 39,791 cases 3,709 were symptomatic 36,082 were asymptomatic (National Health Commission) Deaths, + 1 = 5,233 Learn more about your ad choices. Visit megaphone.fm/adchoices

  • October 5 · 57 min

    Your cancer feedback

    Free download for books and posters, https://drjohncampbell.co.uk/ Hard new copy of the Physiology notes if you live in the UK, https://www.ebay.co.uk/p/86647350 Learn more about your ad choices. Visit megaphone.fm/adchoices

  • October 5 · 1 hr 11 min

    Ivermectin research

    With Professor Colleen Aldous Critical appraisal of multidrug therapy in the ambulatory management of patients with COVID-19 and hypoxemia Part II: Causal inference using the Bradford Hill criteria https://www.jstage.jst.go.jp/article/antibiotics/78/1/78_35/_pdf/-char/en We continue the critical appraisal of three published case series of 119 COVID-19 patients with hypoxemia, treated in the United States, Zimbabwe, and Nigeria with similar ivermectin-based multidrug treatments, to assess the available evidence supporting a causal relationship between treatment and reduction in hospitalizations and mortality. A narrative review was conducted to assess the Bradford Hill criteria for a causal association. We used a previously proposed refinement of the Bradford Hill criteria that reorganized them into three categories of direct, mechanistic, and parallel evidence. The efficacy of the two most aggressive ivermectin-based multidrug protocols is supported by the Bradford Hill criteria for temporality, strength of association, biological gradient, biological plausibility, coherence, consistency, and analogy. The causal relation between the treatment of hypoxemic COVID-19 patients using these protocols and the reduction in hospitalizations and mortality is supported as an inference to the best explanation. Critical appraisal of multidrug therapy in the ambulatory management of patients with COVID-19 and hypoxemia Part I. Evidence supporting the strength of association https://faculty.utrgv.edu/eleftherios.gkioulekas/papers/032-c19-ivm-oxygen.pdf On March 11, 2020, Coronavirus Disease 2019 (COVID-19), the disease caused by the Severe Acute Respiratory Coronavirus 2 (SARS-CoV-2), was declared a pandemic by the World Health Organization (WHO) [1]. Worldwide, 768,187,096 confirmed cases of COVID-19 and 6,945,714 deaths have been reported to the WHO as of June 21 2023, amounting to an average Case Fatality Rate (CFR) of 0.9% [2]. During 2020, while several governments and public health agencies were focused on contagion control and in-hospital patient care, several medical doctors from all around the world innovated and discovered early outpatient multidrug treatments using several repurposed medications in combination [3–15]. In the United States, several independent efforts coalesced into the formulation of a sequenced multidrug protocol [10, Fig. 3] (hereafter, McCullough protocol), which is based on the pathophysiological understanding of COVID-19 as a triphasic illness with three overlapping phases: (1) viral proliferation; (2) hyperinflammatory cytokine storm (COVID-19 pneumonia); and (3) thrombosis. McCullough’s protocol proposed a combination antiviral therapy for treating the viral proliferation phase, immunomodulators for treating the cytokine storm, and antiplatelet agents and antithrombotics for handling the thrombotic stage, based on risk stratification and how the disease presents in each individual patient. Thus, the McCullough protocol is an algorithmic treatment using sequenced multiple drugs in combination and customized to the individual patient and their response to treatment; no single drug is necessary nor sufficient to achieve treatment efficacy towards reducing hospitalizations and deaths. A recently published update of the McCullough protocol [16, Fig. 3] introduced some adjustments including virucidal nasal washes and oral gargles [17–24]. A large case series of 869 high-risk patients [25, 26], who were treated using an early version of the McCullough protocol, has been compared against population-level and historical controls [27], showing the existence of efficacy with respect to the reduction of mortality and hospitalizations, which is also resilient with respect to random selection bias, provided that patients are treated early enough within the first 3 to 5 days from the onset of illness. Indeed, an earli Learn more about your ad choices. Visit megaphone.fm/adchoices

  • October 5 · 16 min

    SAGE omicron leak

    World, now up to 226 confirmed cases in 20 countries Moderna, a material drop in efficacy Pfizer applied to FDA to boost 16 and 17 year olds Pfizer's chief scientific officer, Mikael Dolsten https://www.statnews.com/2021/11/30/pfizer-research-head-envisions-a-sprint-to-develop-omicron-vaccine-if-its-needed/ Enough experimental vaccine to begin a clinical trial within about two months Very high commercial scale, by early March cautiously optimistic, especially for the boosted Pathogenicity https://www.dw.com/en/covid-how-dangerous-is-the-omicron-variant/a-59977618 Preliminary data suggests that there are increasing rates of hospitalization in South Africa, but this may be due to increasing overall numbers of people becoming infected, rather than a result of a specific infection with omicron Professor Salim Abdool Karim, South Africa The vaccine should hold well in terms of preventing hospitalizations The European Union 44 confirmed cases in EU countries https://www.telegraph.co.uk/world-news/2021/12/01/eu-must-consider-mandatory-vaccination-says-ursula-von-der-leyen/ Dr. Ursula von der Leyen, European Commission’s President Must consider mandatory vaccination highly contagious omicron variant 150 million not vaccinated This is an enormous health cost coming along 77 % of adults 66% of whole population Greece and Austria already mandating Netherlands 13 cases US Sewage surveillance FDA Narrow vote (14 to 10) approve Merck molnupiravir Only high-risk patients Not in pregnancy UK 22 cases https://www.telegraph.co.uk/politics/2021/11/30/new-covid-restrictions-last-march-next-year/ New self-isolation rules now law 10 days after contact with omicron Even if fully vaccinated Fine up to £10,000 Until March 24 ? new pingdemic Scientific advisory group for emergencies, leak 30 scientists, Patrick Vallance, Chris Whitty https://www.telegraph.co.uk/global-health/science-and-disease/covid-news-cases-deaths-booster-jab-coronavirus-omicron/ Stringent response measures may be needed for omicron highly likely that omicron, after infection or vaccination to some extent there will be immune escape Expects booster jabs to provide protection for now Future remains highly uncertain potentially very significant wave of infections Covid symptom tracker data https://covid.joinzoe.com/data#levels-over-time WHO advice for international traffic in relation to the SARS-CoV-2 Omicron variant (B.1.1.529) https://www.who.int/news-room/articles-detail/who-advice-for-international-traffic-in-relation-to-the-sars-cov-2-omicron-variant Preliminary evidence suggests an increased risk of reinfection with this variant as compared to other VOCs Current SARS-CoV-2 polymerase chain reaction (PCR) diagnostics continue to be effective Blanket travel bans will not prevent the international spread People not fully vaccinated, sick or at increased risk, should be advised to postpone travel to areas with community transmission Learn more about your ad choices. Visit megaphone.fm/adchoices

  • October 5 · 20 min

    Elevated young deaths, UK and US

    Pfizer expects to hike U.S. COVID vaccine price to $110-$130 per dose https://www.reuters.com/business/healthcare-pharmaceuticals/pfizer-expects-price-covid-vaccine-110-130-per-dose-2022-10-20/ Pfizer executive Angela Lukin Pfizer Inc expects to roughly quadruple vaccine price, to about $110 to $130 per dose, after the United States government's current purchase program expires, U.S. government currently pays around $30 per dose to Pfizer and German partner BioNTech Pfizer Expects the COVID-19 market to be about the size of the flu shot market Tim Gough, 55, Radio Suffolk https://www.telegraph.co.uk/news/2022/10/24/radio-dj-dies-halfway-hosting-breakfast-show/ Excess deaths in the young https://app.powerbi.com/view?r=eyJrIjoiYmUwNmFhMjYtNGZhYS00NDk2LWFlMTAtOTg0OGNhNmFiNGM0IiwidCI6ImVlNGUxNDk5LTRhMzUtNGIyZS1hZDQ3LTVmM2NmOWRlODY2NiIsImMiOjh9 US data https://www.cdc.gov/nchs/nvss/vsrr/covid19/excess_deaths.htm#data-tables US, all ages https://usmortality.com/deaths/excess-cumulative/united-states Tragic young death https://nypost.com/2022/10/08/rep-sean-casten-reveals-teen-daughter-died-from-cardiac-arrhythmia/ https://www.foxnews.com/politics/illinois-rep-sean-casten-reveals-teenage-daughter-died-cardiac-arrhythmia https://www.dailymail.co.uk/news/article-11294477/Illinois-Rep-Sean-Casten-reveals-healthy-teenage-daughter-died-cardiac-arrhythmia.html https://www.cdc.gov/coronavirus/2019-ncov/vaccines/safety/adverse-events.html Gwen Casten, 17, died peacefully in her sleep in June, after eating dinner with her parents and then going out with friends for a few hours. (Congressman Rep. Sean Casten) Democrat’s statement She had just come home from an evening with friends, went to bed and didn’t wake up The Castens This past June, our daughter, Gwen Casten, died of a sudden cardiac arrythmia. In layman’s terms, she was fine, and then her heart stopped healthy 2022 teenager fully vaccinated and had tested positive for COVID-19 more than once in recent months, but never experienced symptoms. She had a big, beautiful, kind, loving heart. And it stopped, as all must China, 20th party congress President Xi Jinping https://www.theguardian.com/world/2022/oct/14/chinas-communist-party-congress-everything-you-need-to-know https://www.bbc.co.uk/news/world-asia-china-63112996 No immediate loosening of zero-Covid strategy Zero-Covid, people's war to stop the spread of the virus Recent weeks Tens of millions, confined home 60 towns and cities Dynamic zero-Covid, linked to Mr Xi Strict lockdowns, mass testing, constant scanning of health codes, travel restrictions Trains out of Xinjiang suspended Roadblocks Widespread reports, food and medicine Quarantine centres, family separations IDs linked to health code apps No vaccine compulsion (Local vaccines only) Professor Liang Wannian, government Covid expert panel Zero-Covid might come to an end? It's hard to say Because one thing I am sure of is, we won't kill the virus any time soon. We're waiting for more effective medicines and more effective vaccines. Learn more about your ad choices. Visit megaphone.fm/adchoices

  • October 5 · 21 min

    Excess Deaths and cancers after vaccine

    Significant Increase in Excess Deaths after Repeated COVID-19 Vaccination in Japan https://pubmed.ncbi.nlm.nih.gov/40416011/ Although Japan recorded the world's highest rate of COVID-19 messenger ribonucleic acid (mRNA) vaccination doses per capita, (3.3 doses, 0 -8) COVID-19 cases and deaths exploded after the emergence of the Omicron variant, (despite more than 80% of the population having been fully vaccinated) followed by a significant increase in excess deaths in 2022 and 2023. Although several hypotheses have been proposed to explain these phenomena, the truth remains to be established because sufficient studies and data disclosures have not been conducted to adequately investigate the possible contribution of mRNA vaccines. The causes of the excess deaths from not only COVID-19 but also other factors after repeated mRNA vaccinations must be elucidated, given this could provide valuable information to help combat future infectious disease outbreaks. Japan, 2022 and 2023, excess deaths per million More than 1,400 (three times higher than that in the United States) COVID-19 deaths in Japan accounted for only 10% of these excess deaths Another hypothesized cause of the excess deaths is various adverse reactions to COVID-19 vaccinations. As of November 18, 2024, Japan After COVID-19 vaccination Government has provided payouts for 8, 432 injuries Payouts after 903 deaths Numbers that are still increasing, already greatly exceed the numbers of injuries and deaths, for which payments were made, after all other vaccinations in the last 47 years. Many injuries and deaths in the young population E.g. fatal case, 14-year-old girl (vaccinate to protect granny) This policy contradicts an early study (August 2021) showing vaccination did not reduce the viral load of infected individuals Adverse reactions reported Myocarditis, pericarditis, blood clotting, and autoimmune diseases linked to lipid nanoparticles (LNPs) and excessive production of spike proteins generated by the mRNA. Deaths from cancers related to estrogen receptors, such as leukemia, breast, pancreatic, lip/oral/pharyngeal, ovarian, and uterine cancers, have also increased since the population-wide administration of mRNA vaccinations Spike protein of SARS-CoV-2 is known to bind to estrogen receptors, located in the nucleus, and includes a nuclear localization signal, which makes it more likely to be conveyed to the nucleus. Another hypothesis involves chronic infection caused by immunosuppression after repeated vaccination. Indeed, recent studies have reported an increase in spike-specific (more immunoglobulin G4, more regulatory T cells) Wastewater monitoring data support this claim. Robert Redfield “The benefit to the 30-year-old firefighter, I don’t see the benefit.” “There’s prolonged production or impact or negative consequence from spike protein in some people that get the mRNA vaccine.” The concerns related to the mRNA-LNP formulation evidently need to be taken seriously. Thus, it is imperative to elucidate the effects of population-wide COVID-19 vaccination. Japanese health authorities have been hesitant to provide data It was revealed that the vaccinated were as susceptible as or even more susceptible to COVID-19 infection than were the unvaccinated Learn more about your ad choices. Visit megaphone.fm/adchoices

  • October 5 · 34 min

    The Australian Plan

    Australia takes the courage of it's convictions US Half a billion free at home lateral flow tests Military (1,000) helping hospitals The omicron virus spread more rapidly than anyone thought Texas One omicron death Man in his 50s Underlying health conditions Unvaccinated Australia https://www.reuters.com/world/asia-pacific/australia-rules-out-lockdowns-despite-omicron-surge-2021-12-21/ NSW, cases + 3,763 Victoria, cases + 1,503 Australian thinking To stop omicron with vaccination, near 100% efficacy with near 100% uptake With no waning Natural infection promotes antibody IgA (vaccines generate IgM then IgG Preventing vial replication in the upper airways Allowing omicron infection up to the point where hospitalisations are manageable Less pathogenic with shorter hospital stays Natural immunity giving cross immunity to the next variant Concurrent booster programme for the elderly and comorbid Over time need for pharmaceutical and NPIs will diminish If hospitalisations do rise, population will self-titrate https://www.doherty.edu.au/our-work/institute-themes/viral-infectious-diseases/covid-19/covid-19-modelling/modelling Millions of Covid cases by the end of January or early February Infections, + 200,000 per day Up to 4,000 hospitalisations a day PM Mr Morrison The modelling assumed the Omicron strain is as serious as Delta Failed to account for boosters or people taking sensible behavioural responses in what they're doing So I wouldn't want to alarm people over that report. That is not what we are actually expecting to happen The grim predictions were highly unlikely There is a range of scenarios, of course the number of Omicron cases will increase. It's highly infectious. But the indications are that it is not as severe and our hospitals, in NSW and Victoria, have been coping extremely well Professor Paul Kelly, Australia chief medical officer https://www.dailymail.co.uk/news/article-10333919/Coronavirus-Australia-Australias-Chief-Medical-Officer-hits-doomsday-Omicron-predictions.html selective and misleading media reporting about ongoing modelling the predicted hospitalisation estimations are unlikely. Evidence about the characteristics of Omicron is still emerging but early trends seen both internationally and within Australia suggest that it is more transmissible However, early indications around hospitalisation, ICU admission and death show that Omicron could be far less than Delta and other variants Importantly, after almost four weeks of Omicron in Australia there are currently no confirmed Omicron cases in ICU and no deaths confirmed to date Modelling, it's one of a range of tools and can't be viewed in isolation A preliminary scenario, of many being considered to help inform decision making Presents one of the worst case of all potential scenarios including assumptions that the Omicron variant is as severe as the Delta variant, an absence of hospital surge capacity, a highly limited booster program, no change to baseline public health and social measures and an absence of spontaneous behaviour change in the face of rising case numbers None of these five assumptions represent the likely state of events, let alone all of them together, therefore presenting that scenario as the likely scenario that will occur is highly misleading Former deputy chief health officer Nick Coatsworth Whoever leaked the Doherty modelling without context has committed a gross injustice to the Australian people Federal Health Minister Greg Hunt Despite the rapid spread of Omicron only a fraction of cases were ending up in hospitals SA hospital data https://www.nicd.ac.za/diseases-a-z-index/disease-index-covid-19/surveillance-reports/daily-hospital-surveillance-datcov-report/ UK data https://coronavirus.data.gov.uk https://www.gov.uk/government/publications/covid-19-om Learn more about your ad choices. Visit megaphone.fm/adchoices

Showing 721–740 of 767 episodes